


OMIM ID:
Alport Syndrome (Collagen IV-Related Nephropathies)
Alternate Names
Defective Genes
Clinical Characteristics
Ocular Features
X-linked Alport syndrome is a basement membrane disease with important ocular manifestations. The lens is usually normal at birth but lens opacities eventually occur in a significant number of individuals with the most characteristic type being anterior polar in location. Involvement of the anterior lens capsule often results in bilateral anterior lenticonus (25%) and may be progressive. It is claimed that the severity of the lenticonus is a valuable marker in judging the overall disease severity. In early stages it may be difficult to detect but its presence is suggested by an ‘oil droplet’ reflex during retinoscopy or slit lamp examination. All males with anterior lenticonus should be evaluated for Alport syndrome.
Posterior polymorphous corneal dystrophy and posterior subcapsular opacities have also been noted. The defect in basement membranes may lead to recurrent corneal erosions, even in children, which can be incapacitating and difficult to treat. Involvement of Bruch’s membrane has been considered the source of retinal pigment epithelial changes described as a flecked retina, or ‘fundus albipunctatus’, found in 85% of patients. More recent evidence using OCT suggests that the dot-and-fleck retinopathy results primarily from abnormalities in the internal limiting membrane and the nerve fiber layer. The yellowish and/or whitish flecks are most commonly located in the posterior pole and particularly in the macula. There is no night blindness or visual impairment from the retinal involvement. Fluorescein angiography shows patchy areas of hyperfluorescence. The amount of visual impairment depends primarily on the extent of lens involvement.
Termporal macular thinning occurs to some extent in all types of Alport syndrome based on OCT findings. In one series all patients with X-linked disease had temporal thinning suggesting that this might be a useful diagnostic sign. However, similar thinning is also seen in Leber hereditary optic neuropathy (535000), and dominant optic atrophy (165500).
Systemic Features
Nephritis with hematuria secondary to basement membrane disease of the glomeruli is the most life threatening aspect of this disorder. It occurs in both sexes but more commonly in males in which it has an earlier onset. Progressive sensorineural hearing loss beginning with high frequencies occurs in many patients, often with subtle onset in childhood, but many adults retain some hearing capacity. In males, the onset of hearing loss often occurs before kidney disease is evident. Hearing loss is less frequent and less severe in females. However, there is considerable clinical and genetic heterogeneity and not all patients have the complete syndrome of nephritis, deafness and ocular disease. In fact, it has been suggested that Alport syndrome can be subtyped into at least six categories based on the extent of organ involvement.
Genetics
Inheritance
Alport syndrome is a member of a group of disorders known as collagen IV-related nephropathies. It is a genetically heterogeneous disease with 85% inherited in an X-linked pattern and most of the remainder occurring in an autosomal recessive pattern and only a few seemingly autosomal dominant. All result from a defect in type IV collagen found in basement membranes. About 80% of cases have a mutation in the COL4A5 gene which is located at Xq22.3. Males seem to be more severely affected than females in the X-linked form of the disease but clearly this disorder affects both sexes reflecting the genetic heterogeneity, much of which remains to be delineated. The autosomal disease generally results from mutations in the COL4A3 or COL4A4 genes and has been seen in both recessive and dominant patterns of transmission.
Pedigree
Autosomal dominant
Autosomal dominant disorders require only one mutation for the disease to be expressed. Since an affected parent has two chromosomes, only one of which has the mutant gene, parents can expect that half (50%) of their children will receive that one and inherit the disease. It is common for individuals that inherit the mutation, however, to not have evidence of the disease (nonpenetrance).
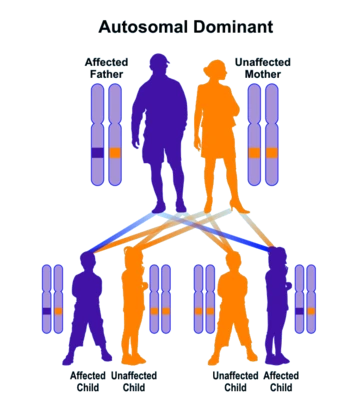
Autosomal dominant inheritance leads to a vertical pattern of transmission
Autosomal recessive
In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.

In order for autosomal recessive disorders to be expressed, offspring generally must inherit two mutations, one from each carrier parent. Carriers with only one mutation, such as the parents, do not have clinical disease. Note that carrier parents can expect that 1 in 4 children (25%) will inherit both mutations and have the disorder, 2 in 4 children (50%) will be carriers like their parents, while 1 in 4 children (25%) inherit neither mutation.
X-linked recessive, carrier mother
X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the mother, she usually does not have the disease since the normal X chromosome without the mutation neutralizes the mutation in the abnormal X chromosome. However, half her sons will inherit the mutation-containing X chromosome and therefore have the X-linked disease. Half the daughters will inherit the mutation-bearing X chromosome and are usuallly healthy 'carriers'.

X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the mother, she usually does not have the disease since the normal X chromosome without the mutation neutralizes the mutation in the abnormal X chromosome. However, half her sons will inherit the mutation-containing X chromosome and therefore have the X-linked disease. Half the daughters will inherit the mutation-bearing X chromosome and are usuallly healthy 'carriers'.
X-linked recessive, father affected
X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the father, he has the disease since his only X chromosome is mutant and he has no normal X to blunt the effects of the abnormal gene. His sons only receive his Y chromosome and thus are all normal. However, all his daughters receive his one and only X chromosome and will be healthy 'carriers'. Thus such males will have no affected children but half their grandsons from those daughters will have the same disease as he does.

X-linked disorders are caused by a mutation on the X chromosome and both sexes can pass this to their children. If the mutation is in a recessive gene and carried by the father, he has the disease since his only X chromosome is mutant and he has no normal X to blunt the effects of the abnormal gene. His sons only receive his Y chromosome and thus are all normal. However, all his daughters receive his one and only X chromosome and will be healthy 'carriers'. Thus such males will have no affected children but half their grandsons from those daughters will have the same disease as he does.